
Can a Heavy School Backpack Make Scoliosis Worse? What Parents Should Know
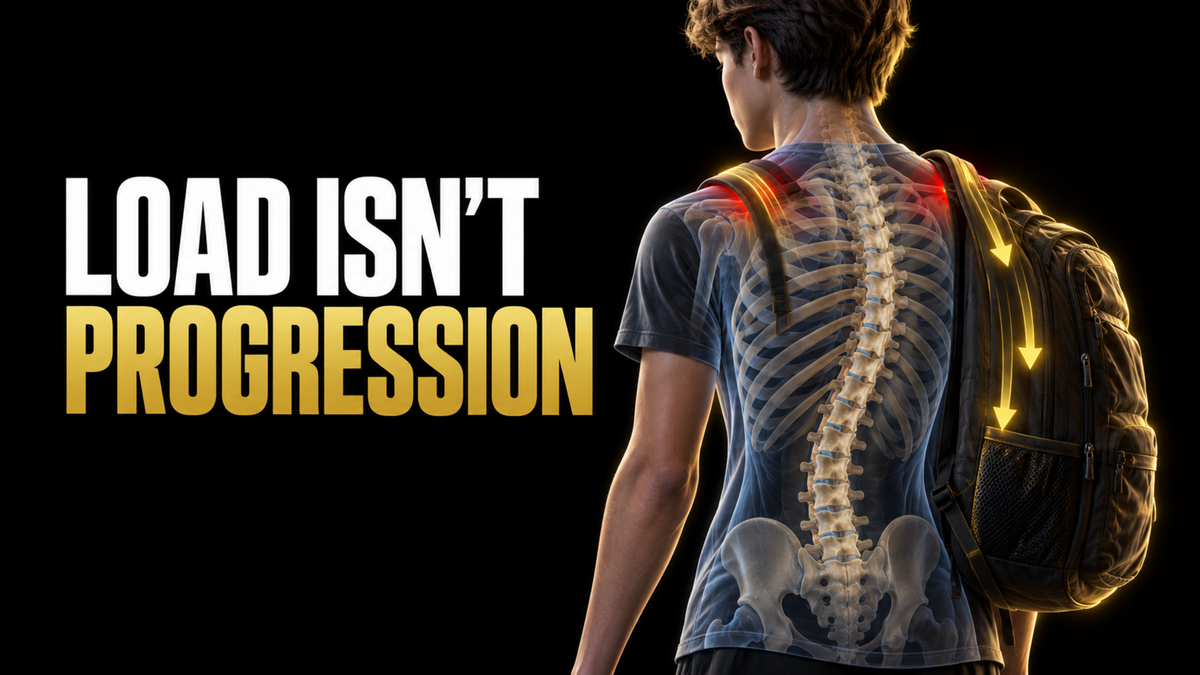
Surgery fears grow quickly when a parent notices their teenager leaning forward under a heavy school bag, one shoulder appearing higher, or back pain getting worse after school. If scoliosis has already been diagnosed, it is understandable to wonder whether the backpack is compressing the spine and making the curve progress.
The direct answer is more reassuring and more nuanced: a heavy or poorly fitted backpack can change posture while it is being carried, increase fatigue, and contribute to shoulder, neck, or back discomfort. However, current evidence does not establish ordinary backpack use as a cause of adolescent idiopathic scoliosis or as a driver of structural curve progression.
That does not mean the backpack should be ignored. It means parents need to separate two different issues: the temporary response to an external load and the underlying three-dimensional scoliosis presentation. This guide explains how backpacks affect posture, how heavy is too heavy, what changes when scoliosis or a brace is already present, and when a child needs a fuller assessment rather than another bag adjustment.
Short answer: A heavy backpack may increase strain and temporarily alter how a teenager stands or walks. It is not the same as the spine structurally worsening. Persistent asymmetry without the bag, new symptoms, or documented Cobb-angle progression should be assessed separately.

Figure 1. Backpack load can affect posture and comfort while it is carried, but this is not the same as structural scoliosis progression.
Table of Contents
- Can a heavy backpack cause or worsen scoliosis?
- What a backpack changes under load
- Temporary posture versus structural progression
- How heavy should a school backpack be?
- One strap versus two straps
- How to fit and pack the bag
- Special considerations for scoliosis and bracing
- Why the backpack may not be the whole problem
- Warning signs parents should not ignore
- Practical weekly backpack check
- Conclusion
- About the Author
- Frequently Asked Questions
Can a Heavy Backpack Cause or Worsen Scoliosis?
There is no good evidence that an ordinary school backpack causes adolescent idiopathic scoliosis. Idiopathic scoliosis is a three-dimensional spinal condition that most often becomes apparent during growth. Its development and progression are discussed in relation to factors such as growth remaining, skeletal maturity, curve magnitude, curve pattern, and biological influences—not simply the type of bag a child carries.
The Scoliosis Research Society explains that heavy backpacks do not cause scoliosis or make the condition worse. The American Academy of Pediatrics also states that backpacks have not been shown to cause scoliosis or other long-term spinal problems, although poor use can contribute to pain and strain.
Parents did not cause their child's scoliosis by buying the wrong backpack. Better backpack habits may improve comfort, but the bag should not be treated as either the cause of scoliosis or a correction tool.
What about an existing curve?
A child who has scoliosis may respond differently to the same load. The bag can make a trunk shift, shoulder difference, forward lean, or fatigue more obvious. A teenager with pain, reduced endurance, or a brace may tolerate less weight.
That visible response still does not prove that the Cobb angle has changed. Curve progression is evaluated through appropriate medical follow-up, growth status, clinical examination, and comparable imaging—not by how crooked a child looks while carrying books.
Parents worried about a changing curve should also understand what drives scoliosis progression during puberty and why growth stage matters.
What a Backpack Changes Under Load
The body must keep its combined center of mass over the feet. When weight is placed behind the trunk, the teenager may lean forward, extend the head, adjust the pelvis, shorten the stride, or change arm movement to remain balanced. Heavier loads and longer carrying times can make those adaptations more noticeable.
A study involving schoolgirls with mild adolescent idiopathic scoliosis and age-matched controls found that increasing backpack load increased trunk flexion, changed head position, and affected balance. The authors reported similar sagittal-plane postural changes in both groups, while the scoliosis group showed some different balance characteristics. This supports sensible load management; it does not show that backpacks produce permanent curve progression.
A systematic review of backpack loads and postural deviation found that many studies report postural changes under heavier loads. It also noted important limitations: small samples, varied methods, and no perfectly established universal cutoff.

Figure 2. The body may lean forward and reorganize under load to keep balance; posture under load should not be confused with a permanent structural change.
Temporary posture is not the same as structural progression
Posture under load describes what happens while the external weight is present. Structural scoliosis includes a persistent lateral curve and vertebral rotation. Removing the backpack removes the external load, but it does not remove structural scoliosis.
This gives parents a useful home observation—not a diagnosis. Watch the child walk with the backpack and then observe them standing naturally without it. If the forward lean disappears after the bag is removed, the load probably contributed to that temporary posture. If an uneven shoulder, waist difference, trunk shift, or rib prominence remains, it deserves separate attention.
An X-ray remains important for measuring the curve, but it does not fully describe movement or muscular behavior. Our guides to Cobb angle versus spinal rotation and what scoliosis X-rays miss explain why teenagers with similar measurements may look and move differently.
How Heavy Should a Child's Backpack Be?
Many pediatric resources use approximately 10% to 15% of body weight as a practical screening range. The American Academy of Pediatrics advises that a backpack should not exceed 15% of the child's body weight. A 40 kg teenager would therefore have a 6 kg upper screening limit at 15%, while 10% would be 4 kg.
That number is not a guarantee. Pain, a long walk, stairs, a brace, fatigue, and carrying tolerance all matter. Research has not established one perfect threshold for every student.
Combine the scale with observation. The bag is too demanding when the child leans markedly forward, struggles to lift it, has pain or numbness, loses normal walking rhythm, or feels unusually exhausted.

Figure 3. Ten to fifteen percent of body weight is a practical screening range, not a universal safety guarantee for every child.
Duration matters too
The same weight carried for two minutes is different from carrying it for thirty minutes and up stairs. Consider carrying time, distance, school layout, extra equipment, and brace use. The goal is the lightest practical school-day load.
One Strap Versus Two Straps
Carrying a bag on one shoulder creates an asymmetric external load. The teenager may lift one shoulder, side-bend the trunk, grip the strap, or shift the pelvis to keep the bag from sliding. These compensations may contribute to local fatigue and may make an existing asymmetry look more noticeable.
Two shoulder straps generally distribute weight more evenly and keep the load closer to the body. Broad, adjustable straps can reduce concentrated pressure. A chest strap can limit side-to-side movement, while a correctly fitted waist strap may transfer some load toward the pelvis.
This recommendation is about comfort and load distribution—not scoliosis correction. Parents should not choose a carrying side based only on the direction of a curve. Rules such as “carry it on the higher shoulder” or “use the opposite side to balance the spine” ignore vertebral rotation, pelvic position, strength differences, and the child's actual movement strategy.

Figure 4. Two evenly adjusted straps usually distribute school-bag load more evenly than one-shoulder carrying.
How to Fit and Pack a School Backpack
Choose the right size
- Choose a child-sized bag rather than an oversized adult backpack.
- The bag should sit close to the back and should not hang far below the waist.
- Look for two broad, padded, adjustable shoulder straps.
- Use compartments so heavy items do not collect in one corner.
- Consider a chest or waist strap for longer walks when it is comfortable.
Place heavy items close to the body
Textbooks, tablets, and laptops should sit in the compartment closest to the back. Smaller items should be distributed rather than concentrated in one outer pocket. Remove old notebooks, duplicate stationery, unused chargers, sports equipment, and full water bottles that are not required that day.
Adjust both straps
Both straps should be similar in length and snug enough to stop the bag bouncing away from the back. They should not be so tight that they cause pressure, tingling, or restricted shoulder movement. Teach the teenager to lift the bag from a stable surface and use both straps instead of twisting while swinging a heavy bag onto one shoulder.
Reduce weight at the source
Good technique cannot compensate for unnecessary weight. Ask the school about lockers, duplicate textbooks, digital resources, classroom storage, or leaving sports equipment on site. A rolling bag may help some children when school rules, stairs, and crowded corridors allow it.
Special Considerations for a Teenager With Scoliosis
A scoliosis diagnosis does not automatically make a child fragile. Many teenagers remain active. Our guide to sports participation for teenagers with scoliosis explains the role of symptoms, medical restrictions, and movement quality.
However, the same backpack may feel different to two teenagers with scoliosis. One may tolerate it easily. Another may already have pain, fatigue, a trunk shift, a rib prominence, reduced endurance, or sensitivity from a brace. The bag should be adjusted according to the child's response rather than a universal rule based on curve direction.
If the teenager wears a scoliosis brace
A brace changes how the backpack contacts the body. Shoulder straps, the lower edge of the bag, or hard objects inside it may create pressure, rubbing, heat, or skin irritation. The bag may also sit farther away from the body.
Follow the orthotist's and medical team's instructions. Test the packed bag while the brace is being worn, inspect the skin after the school journey, and report persistent redness, skin breakdown, numbness, or increasing pain. Do not cut, heat, reshape, or add unapproved padding to the brace based on general online advice.
Practical changes may include lowering the bag weight, adjusting strap width and length, using school storage, or changing the bag style. Bracing decisions remain medical decisions.
Why the Backpack May Not Be the Whole Problem
Changing a backpack can solve a backpack problem. It cannot identify the teenager's full scoliosis pattern, measure Cobb-angle progression, assess skeletal maturity, or determine which muscles need more strength or control.
This matters when a family has already tried generic stretches, massage, general physical therapy, or online exercises but still sees asymmetry or limited progress. A temporary reduction in discomfort does not automatically address the child's three-dimensional rotation, pelvic position, strength differences, or movement strategy.
The muscular pattern should be assessed rather than assumed. Concave and convex describe curve geometry; they do not automatically reveal which muscles are weak, tight, overactive, or underactive. The same side-specific instruction may be appropriate for one person and unnecessary for another.
Within the SpineX™ Method, individualized assessment comes first. Posture, visible rotation, pelvic alignment, muscular asymmetry, movement quality, symptoms, training history, and medical context are considered together. When appropriate, personalized online scoliosis training may then use unilateral strength training, 3D de-rotation principles, and progressive exercise programming based on the assessment findings.
Exercise does not guarantee Cobb-angle reduction or surgery avoidance. It should match the person instead of a generic formula. Read when to consider an individualized scoliosis assessment if your teenager's plan feels disconnected from how they move.

Figure 5. Persistent asymmetry should be assessed without assuming that the backpack is the cause.
Warning Signs Parents Should Not Ignore
Occasional fatigue after a long school day is different from persistent or worsening symptoms. Arrange an appropriate medical evaluation if your child develops:
- persistent or worsening back pain;
- pain that wakes them at night;
- weakness, numbness, or tingling;
- changes in walking or balance;
- bowel or bladder changes;
- unexplained fever;
- breathing difficulty;
- symptoms after a major fall or trauma;
- rapidly changing visible asymmetry.
Also seek review if a shoulder or hip difference, rib prominence, trunk shift, or uneven waist remains when the teenager stands without the backpack. A school bag may draw attention to an asymmetry, but it should not automatically be blamed for it.
If scoliosis is already diagnosed, keep scheduled clinical reviews and recommended imaging. The school accommodations guide can help families discuss storage, extra transition time, seating, brace needs, and other practical support with the school.
A Two-Minute Weekly Backpack Check
- Empty it. Remove old papers, unused books, duplicate stationery, chargers, and equipment from previous days.
- Pack it. Place the heaviest items closest to the back and balance smaller items between compartments.
- Weigh it. Use 10% to 15% of body weight as a practical screening range while also considering symptoms and carrying time.
- Fit it. Adjust both straps evenly and use the chest or waist strap when available and comfortable.
- Watch the walk. Look for marked forward lean, unusual shoulder elevation, altered steps, bag sway, or repeated strap adjustment.
- Ask directly. “Does anything hurt, feel numb, rub, or make you unusually tired?”
- Observe without the bag. Persistent asymmetry should be considered separately from the temporary response to carrying.
Practical Takeaways
- School backpacks are not established as a cause of adolescent idiopathic scoliosis or structural curve progression.
- A heavy or poorly fitted backpack can change posture during carrying and may contribute to pain or fatigue.
- Two straps, a close fit, and lighter daily contents usually improve load distribution.
- The 10% to 15% guideline is a screening tool, not a universal safety threshold.
- Do not use one-sided carrying as a homemade corrective strategy.
- A backpack adjustment cannot replace orthopedic follow-up or individualized assessment.
- Persistent asymmetry without the bag, neurological symptoms, worsening pain, or brace-related skin problems require appropriate review.

Conclusion
At SpineX, we don't prescribe the same exercises for every person with scoliosis. The SpineX™ Method is a proprietary fitness-based scoliosis training system built on unilateral strength training, 3D de-rotation principles, individualized assessment, and fully personalized, progressive exercise programming. Every scoliosis is different, which is why each person's curve pattern, muscle imbalances, movement limitations, and goals require an individualized approach.
If you've made it this far, you're probably not just curious — you're looking for something that actually applies to you, or to your child, instead of another generic list that never quite fits. That's exactly what an individualized assessment is for. You don't need to guess, and you don't need to keep training blind. The SpineX Surgery-Avoidance Assessment is a live, one-on-one video call from wherever you are — no equipment, no clinic visit, just simple movement checks like bending forward and rotating side to side, so we can actually see how your body moves before recommending anything. Book your Surgery-Avoidance Assessment and finally get answers built around your spine, not a generic formula. You can also explore the SpineX™ 3D Scoliosis Method to see how a personalized program comes together once your assessment is complete.
About the Author
Kamil is the founder of SpineX and creator of The SpineX™ 3D Scoliosis Method — a proprietary fitness-based scoliosis training system. His methodology combines unilateral strength training, 3D de-rotation principles, individualized assessment, and fully personalized, progressive exercise programming to help people with scoliosis improve movement quality, build strength, address muscle imbalances, reduce three-dimensional spinal asymmetries, and support long-term spinal health through non-surgical management.
Through SpineX, Kamil has worked with clients worldwide, providing personalized online coaching, educational resources, and evidence-informed exercise strategies for scoliosis, kyphosis, posture, and spinal asymmetries.
Frequently Asked Questions
1. Can a heavy backpack make my child's scoliosis curve worse?
A heavy bag can change posture and increase fatigue while it is carried. That is not the same as structural curve progression. Current guidance does not establish ordinary backpack use as a cause of scoliosis or worsening Cobb angle. Progression should be evaluated through medical follow-up, growth status, examination, and comparable imaging. Lighten an uncomfortable load, but do not use bag adjustments as a substitute for orthopedic review.
2. What percentage of body weight is appropriate for a school backpack?
Ten to fifteen percent of body weight is a practical screening range, and the American Academy of Pediatrics advises staying at or below 15%. It is not a universal guarantee: symptoms, brace use, walking distance, stairs, and fatigue affect tolerance. Reduce the load if the child leans markedly forward, struggles to lift it, has pain or numbness, or cannot walk normally.
3. Can carrying a backpack on one shoulder cause scoliosis?
One-shoulder carrying creates an asymmetric external load and may cause temporary shoulder elevation, trunk side-bending, pelvic shifting, or local fatigue. It has not been shown to cause adolescent idiopathic scoliosis. For routine school use, two evenly adjusted straps usually distribute the load more comfortably. Do not deliberately choose one side as a scoliosis correction strategy based only on the curve direction, because the X-ray does not fully reveal the teenager's rotation, pelvic alignment, muscular pattern, or movement strategy.
4. Can a backpack cause uneven shoulders or a rib hump?
A heavy or one-sided bag can temporarily make one shoulder look higher and can produce a visible trunk shift while it is being carried. A rib prominence associated with scoliosis relates to the three-dimensional rotation of the trunk rather than simply the pressure of a strap. Observe the teenager standing naturally and bending forward without the backpack. If the asymmetry remains, becomes more noticeable, or changes over time, discuss it with an appropriate healthcare professional instead of assuming the bag caused it.
5. Is a rolling backpack better for scoliosis?
A rolling backpack may help a teenager who develops pain or fatigue with a conventional bag. It is not always practical: stairs, uneven ground, crowded corridors, storage rules, and pulling with one arm matter. If permitted, test the actual route and choose it for comfort—not as a treatment expected to correct scoliosis.
6. How should a backpack fit over a scoliosis brace?
The bag should sit securely without concentrated pressure, rubbing, numbness, or interference with the brace. Test the fit while the brace is actually being worn, use two broad straps, and reduce unnecessary weight. Because brace designs differ, the orthotist or treating medical team should guide brace-specific adjustments. Do not alter the brace or add unapproved padding based on general online advice. Persistent redness, skin breakdown, increasing pain, or reduced brace tolerance should be reported to the responsible clinician or orthotist.
7. Can strengthening make carrying a school bag easier?
Improving physical capacity and muscular control may help a teenager tolerate ordinary daily tasks, including walking and carrying. For scoliosis, however, strengthening should not be reduced to a generic “strong back” routine or a presumed weak side. Exercise selection, side, loading, range of motion, repetitions, and progression should depend on individualized assessment. Training may improve strength, control, movement quality, and function, but it should not be presented as a guaranteed way to change a structural curve or prevent progression.
8. Should my child carry the backpack on the side opposite the curve?
There is no universal corrective side for carrying a school bag. Curve direction alone does not reveal which muscles are weaker, tighter, more active, or less active. It also does not fully describe vertebral rotation, pelvic position, shoulder behavior, or walking compensation. Loading one side intentionally may simply create another asymmetric demand. For ordinary school use, two straps adjusted evenly are the clearest starting point. Any side-specific exercise or loading strategy should come from an adequate assessment rather than a generic concave-versus-convex rule.
9. When should backpack-related pain be checked medically?
Seek medical advice when pain is persistent, worsening, severe, linked to trauma, wakes the teenager at night, or occurs with weakness, numbness, tingling, walking changes, fever, breathing difficulty, or bowel or bladder symptoms. Reduce or remove the bag while arranging evaluation. If scoliosis is already diagnosed, new pain should not automatically be attributed to either the curve or the backpack. A proper history and examination are necessary, especially when neurological or systemic warning signs are present.